Orthosmile Hounslow Dental Implants: A Practical Guide
This guide explains how Orthosmile Hounslow supports patients considering dental implants and orthodontics. It provides objective background on implant care, outlines how low-cost implant paths work across English- and Portuguese-speaking markets, and includes a country-by-country cost reference. You’ll also find a step-by-step checklist, a comparison of information sources, and FAQs to help you plan responsibly.

1) Executive summary: what patients usually need to know first
If you are researching Orthosmile Hounslow for dental implants or related orthodontic care, the very important practical question is not “How cheap can it be?”—it is “Which clinical plan is appropriate for my bone, bite, and timeline?” Dental implants typically require a staged process (assessment → planning → surgery → restoration). A “low-cost” approach can sometimes be achieved through treatment selection, efficient protocols, or insurance planning, but it should never compromise core clinical requirements such as implant stability, infection control, properly designed prosthetics, and a maintenance plan that protects the long-term health of gum tissue around the implant.
In practice, many patient disappointments happen when quotes appear to cover only the implant fixture, while the real cost drivers—imaging, surgical support, bone augmentation, abutment components, crown/bridge materials, bite adjustments, and follow-up—are billed separately later. Before you compare providers, you should ask: “What exactly is included in the total treatment pathway, and what variables could change that pathway once you review my scans and exam?”
In this guide, you’ll find:
- An expert-oriented framework for evaluating implant options near Hounslow
- Objective background on low-cost dental implant information sources and how to interpret them
- Country-level reference cost ranges for single-tooth implants (planning purposes only)
- A step-by-step guide to pursuing lower-cost dental implants in English-, Spanish-, and Portuguese-speaking countries
- FAQs aligned to real-world patient decision points (including “what to ask,” “what’s missing,” and “what could go wrong”)
- A documentation checklist so you can compare clinics fairly
Throughout, the focus is on clarity and patient safety: you should be able to understand why a plan is being recommended, how success is measured, and what happens if results don’t go as expected.
2) Background on Orthosmile Hounslow and why “implants + alignment” often connect
Many patients discover Orthosmile Hounslow while searching for solutions that cover more than one concern—for example, missing teeth alongside bite misalignment, shifting teeth after tooth loss, poor chewing efficiency, or a desire for more confident aesthetics. It’s common to see implant and orthodontic goals intersect because the mouth is a mechanical system: when teeth are missing, spaced, or angled incorrectly, the way forces distribute during chewing changes, and restorative planning must adapt accordingly.
That said, the relationship between implants and alignment is highly individualized. In some patients, orthodontics is helpful or even necessary; in others, implant placement and restorative design can be performed without orthodontic treatment. A responsible clinic plan typically documents why the chosen pathway fits your specific circumstances.
Three frequent reasons implants and orthodontics connect:
- Tooth loss can change bite dynamics. When a tooth is missing, adjacent teeth may drift, opposing teeth may over-erupt, and chewing patterns can become less balanced. Over time, this can make it harder to place an implant in an ideal restorative position without complications or awkward crown angulation.
- Alignment can influence implant outcomes. Orthodontic assessment may be needed to create space, coordinate tooth positions, or improve prosthetic alignment—particularly when replacing teeth in the aesthetic zone (front teeth) or when multiple teeth are missing and a coordinated bite is required.
- Timing matters. In some cases, orthodontics is performed before implant placement to improve spacing and occlusal relationships. In others, orthodontics is coordinated afterward (or used minimally) to fine-tune alignment so the final restoration looks and functions properly.
From a practical decision standpoint, your first goal is to identify whether orthodontics is:
- Necessary to achieve the right implant position and crown alignment,
- Optional (a refinement that could be helpful but not mandatory), or
- Unrelated (implant placement and restoration can be designed without orthodontic repositioning).
From an industry perspective, a responsible clinic plan typically documents three elements clearly: (1) medical and dental eligibility, (2) implant/prosthetic design logic, and (3) follow-up schedule. If those elements are not transparent, the patient should ask more questions before proceeding—especially if the quote is presented as “low cost” but lacks clarity on diagnostics, restoration design, or maintenance.
3) How dental implants are typically structured clinically (without assuming a “one size fits all” plan)
Dental implants generally consist of a titanium (or titanium-based) implant fixture placed into the jawbone, an abutment that connects implant and restoration, and the final crown/bridge/denture component. Very clinical pathways also include imaging and surgical planning to ensure proper implant position, safe distances from anatomical structures, and a prosthetic outcome that supports bite stability and long-term gum health.
It can help to think of implant therapy in terms of predictable stages, even though the exact order can vary:
Common stages include:
- Comprehensive assessment: clinical exam, periodontal evaluation, oral hygiene status, and risk review. Risk review may include smoking history, diabetes control, medications, previous periodontal disease, and any habits that impact healing.
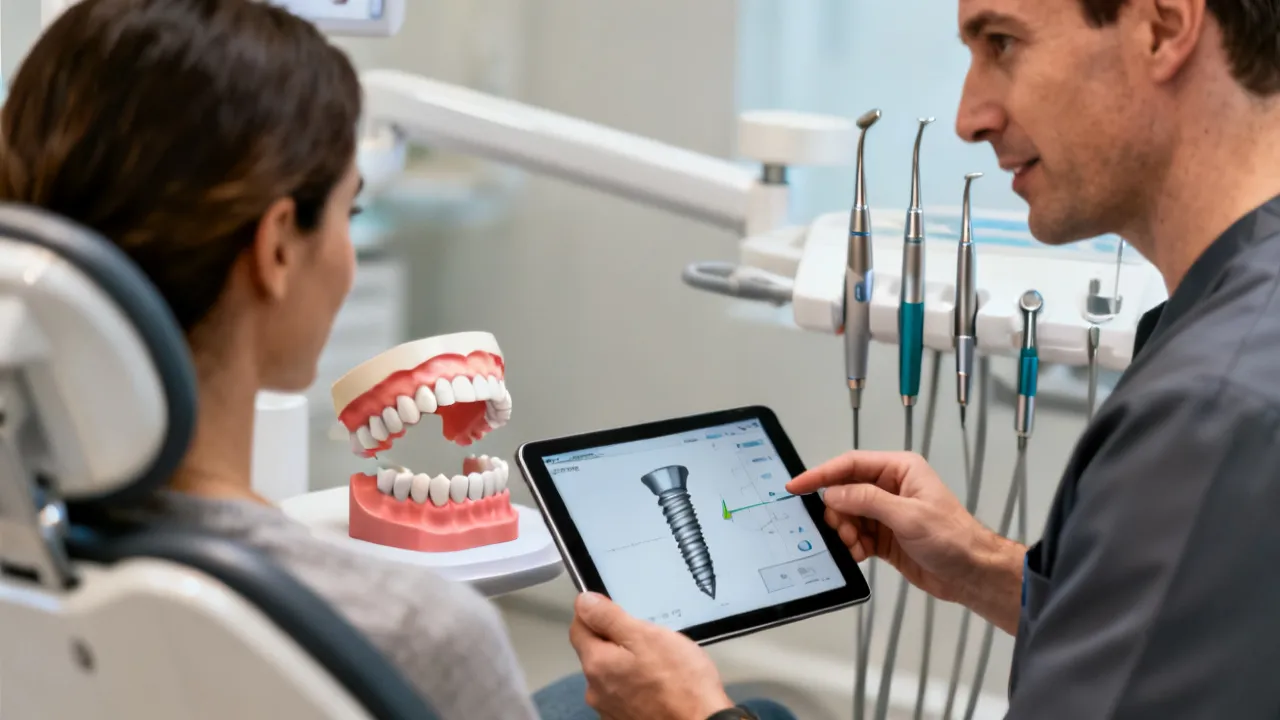
- Imaging and treatment planning: typically cone beam CT (CBCT) or equivalent imaging when appropriate, alongside bite and aesthetic evaluation. Planning should consider the ideal prosthetic position, then translate that into a surgical implant position.
- Implant placement: surgical procedure with infection control and primary stability goals (for example, achieving adequate torque stability where indicated).
- Osseointegration and healing: time for bone integration and tissue maturation. Healing may be conventional (delayed restoration) or immediate (depending on stability and clinical scenario).
- Restoration: crown/bridge fabrication, occlusal adjustment, and aesthetics-focused fit. This stage includes verifying that the bite contact pattern supports comfort, durability, and gum health.
- Maintenance: good recall, hygiene coaching, and monitoring of peri-implant tissues (including probing where appropriate and assessing inflammation).
Where cost discussions usually go wrong: Some “low-cost” marketing focuses heavily on the implant fixture price and underemphasizes planning imaging, surgical support, restoration materials, and follow-up. Patients may be told “the implant is affordable,” but not told that additional steps—like bone grafting, sinus lift (for certain posterior upper jaw scenarios), bone contouring, or guided surgery—may be required based on their anatomy and restorative needs.
To make low cost meaningful, you want to know the difference between:
- Low cost achieved by efficiency and appropriate selection (for example, bundling visits while still doing necessary diagnostics), and
- Low cost achieved by omission (for example, skipping imaging, using a plan not tailored to anatomy, or limiting follow-up).
Clinically, peri-implant disease prevention depends on more than the implant fixture; it depends on design, material compatibility, hygiene access, patient education, and aftercare protocols.
4) “Low cost” in dental implants: what it can mean (and what it should not)
“Low-cost dental implants” usually refers to one or more of the following:
- Efficient treatment bundling (for example, reducing redundant appointments while maintaining standards and appropriate assessments).
- Selective clinical pathways (such as choosing an implant approach that matches bone volume and prosthetic needs, rather than automatically recommending complex solutions).
- Insurance planning or financing structures that reduce monthly out-of-pocket expenses, even if total treatment cost remains similar.
- Dental tourism where patients travel to countries with different fee structures and sometimes find packages that bundle surgery and prosthetic fabrication.
- Digital workflow efficiencies (for example, using certain planning software or streamlined processes) that may reduce staff time while still supporting accurate implant positioning and restoration fabrication.
However, “low cost” should not mean:
- Skipping essential diagnostics when your anatomy requires it
- Compromising implant position, which can lead to poor crown angulation, difficult cleaning access, and long-term gum inflammation
- Cutting corners on infection control or surgical protocols
- Selecting restorations without considering good occlusion and peri-implant tissue management
- Providing inadequate follow-up for monitoring healing and early complications
Because peri-implant health depends on biologic factors, design, and maintenance, a low-cost quote that doesn’t clearly include a maintenance and monitoring plan may represent incomplete value rather than real affordability.
It can also be helpful to define what “success” means to you. For many patients, success is not only “the implant is placed” but also:
- A stable, functional bite
- Comfort during chewing and speaking
- Gum tissue that remains healthy over time
- A restoration that looks natural and fits well
- Clear instructions and predictable follow-up
A “low cost” approach that threatens any of these areas may produce a false economy if you later need revision, additional grafting, or replacement of prosthetic components.
5) Reference cost ranges for a single dental implant (planning-only)
Below are cost ranges for individual dental implants only across selected language groups and regions. These figures are included for reference while you compare planning scenarios; final pricing depends on clinical complexity, region, provider approach, implant system choice, bone quality, whether augmentation is needed, and restoration requirements.
Important: A single-tooth implant quote in everyday life may include different components depending on the clinic. Some quote the implant fixture only; others include abutment and crown. Your goal when comparing is to ensure you compare “the same thing” rather than just the cheapest line item.
| Country | Currency | Price range (single implant reference) |
|---|---|---|
| United States | USD | $3,000 - $6,000 |
| United Kingdom | GBP | £2,000 - £2,500 |
| Australia | AUD | AU$3,500 - AU$6,500 |
| Canada | CAD | CA$3,000 - CA$5,500 |
| Spain | EUR | €1,500 - €2,500 |
| Chile | CLP | CLP$800,000 - CLP$1,500,000 |
| Mexico | MXN | $15,000 - $25,000 |
| Colombia | COP | $2,000,000 - $4,000,000 |
| Peru | PEN | S/ 3,000 - S/ 6,000 |
| Argentina | ARS | $80,000 - $150,000 |
| Brazil | BRL | R$3,000 - R$8,000 |
| Portugal | EUR | €1,000 - €2,000 |
| Germany | EUR | €2,000 - €3,500 |
| France | EUR | €1,500 - €2,500 |
| Italy | EUR | €1,500 - €3,000 |
| Japan | JPY | ¥300,000 - ¥700,000 |
To use these numbers wisely, pair them with a checklist of what else you may pay for in your scenario. For example:
- If you have insufficient bone, you may need augmentation, which can significantly increase total cost.
- If you require a bridge because of multiple missing teeth, the “per implant” cost may not predict total expense.
- If you need special materials or aesthetic enhancements, the restoration cost can change.
Reference ranges can help you establish a ballpark, but they cannot replace a personalized assessment.
6) Information sources comparison (what each one helps you with)
To make low-cost research more structured, it helps to distinguish between: (a) clinics that provide treatment, (b) insurance-oriented platforms, and (c) informational portals that help you compare costs and process steps. The key is that each source type answers different questions.
For example, some websites help you understand implant types and general cost drivers, but they may not provide individualized diagnostic criteria. Conversely, a full-service clinic website may explain procedures in detail, but you may not learn how “low cost” they can be until you request an itemized quote based on imaging.
The table below summarizes what several well-known websites tend to emphasize.
| Website type (example) | What it typically clarifies for patients |
|---|---|
| Low-cost implant information portals | Common implant benefits, typical process overview, and general expectations about cost drivers |
| Full-service dental clinic websites | Service scope (implants, orthodontics, cleanings, emergencies), appointment pathways, and care team context |
| Dental tourism aggregators | Cross-border planning considerations, cost-comparison framing, and travel logistics support |
| Dental insurance-focused resources | How to identify coverage options and how insurance can reduce out-of-pocket implant-related spending |
| Language-localized clinical content | Patient-friendly explanations in local languages, supporting comprehension for international patients |
How to interpret these sources without getting misled:
- Look for itemized clarity. If you can’t find which components are included (imaging, abutment, crown, follow-up), treat any “low cost” claim as incomplete.
- Check whether the content is clinical or marketing-only. Clinical content tends to discuss risks, prerequisites, maintenance, and decision criteria.
- Beware of “too fast” timelines. Implant therapy often needs healing periods. If a website promises outcomes without acknowledging healing and diagnostic prerequisites, ask for details.
- Compare based on process, not just price. Two quotes can have the same implant fixture cost but different total value if one includes comprehensive diagnostics and restorative planning while the other doesn’t.
Source list for the information above:
source: www.dentalviews.com
source: www.atlanticdentalgrp.com
source: www.dentavacation.com
source: rockvilledentalarts.com/es
7) Low-cost dental implant pathways in English-, Spanish-, and Portuguese-speaking markets (step-by-step)
This section outlines a practical, clinician-minded workflow you can use when comparing lower-cost routes. It is written to be language-inclusive for patients exploring options in English-, Spanish-, and Portuguese-speaking contexts, whether you are staying local around Hounslow or considering cross-border planning.
When you pursue lower-cost care, you are not only comparing money—you are also comparing risk management, follow-up reliability, and how well your provider can explain their choices. A step-by-step method helps you make these comparisons fairly.
Step 1: Define the clinical goal (single implant vs. full arch, immediate vs. delayed)
- Ask whether your goal is a single implant, multiple implants, or full-arch restoration. Total cost and planning complexity can change substantially.
- Confirm whether “immediate placement” is clinically suitable or whether staged healing is recommended. Immediate approaches are not automatically wrong, but they require specific prerequisites (for example, stability, bone conditions, and infection risk evaluation).
- Request an explanation of why that approach is chosen for your bone and bite. You are aiming for an individualized rationale, not a template.
- Consider whether the missing tooth involves aesthetic concerns (front teeth), functional concerns (posterior teeth and chewing forces), or both. This influences restorative design and materials.
Step 2: Request diagnostics before shopping for price
- Obtain imaging and a documented plan that explains implant positioning. If a provider gives pricing before imaging, ask what assumptions they are using and how the plan might change after scanning.
- If bone volume is limited, ask whether augmentation is needed and whether it is included in the quoted cost. If it’s not included, ask for a range and the criteria that decide augmentation.
- Confirm how peri-implant risk is managed (for example, periodontal disease control, hygiene assessment, and follow-up). If you have active gum disease, treating that first can be a cost-saving strategy long term because it lowers complication rates.
- Ask whether you need a pre-treatment workup such as dental cleaning, periodontal therapy, and stabilization of oral health before surgery.
- Confirm whether digital planning (e.g., CBCT-based planning and/or guided surgery) is used when appropriate, and what that adds to accuracy and safety.
Step 3: Build a “true cost” list (not just the implant fixture)
Low-cost discussions should include:
- Imaging/planning costs (CBCT scans, radiographs, any diagnostic models)
- Surgical fees and materials (including components used during surgery)
- Healing appointments and assessment
- Abutment and the final crown/bridge component
- Occlusal adjustment and the clinic’s warranty or follow-up policy
- Maintenance and hygiene support (recall intervals, professional cleanings, monitoring)
- Contingency steps (what happens if you need a bone graft, if there is sinus involvement, or if you require a different restorative solution)
Practical tip: Ask for the quote in writing and request that it is itemized by stage. If you cannot receive an itemized breakdown, ask whether the clinic can offer a written treatment plan summary. Verbal explanations are not enough when you are making a cost decision.
Step 4: Compare service models (clinic care vs. travel packages vs. insurance)
- Local clinic model: You may pay more upfront but have continuity of care. That can matter if you need adjustments, additional follow-up, or if complications occur.
- Dental tourism model: You typically trade continuity for different fee structures. Travel can be less comfortable after surgery, and aftercare coordination becomes a major factor. You should have a clear plan for what happens if you need an earlier review than the travel schedule allows.
- Insurance and financing model: Use coverage tools to determine eligibility and reduce out-of-pocket implant-related spending within defined rules. Insurance coverage varies widely; pre-authorization may be required.
- Hybrid model: Some patients combine local diagnostics with cross-border surgery/restoration (or vice versa). This can be cost-effective if the communication between providers is strong, but it can also be risky if responsibilities are unclear.
Step 5: Verify credentials and clinical governance
For patient safety, confirm:
- Professional qualifications of the implant surgeon and restorative dentist (and whether those roles are clearly defined)
- Quality controls for imaging and surgical protocols (for example, how they verify implant position and patient safety before and after surgery)
- Materials used for the implant and prosthetic components (what implant system, what abutment type, what crown material)
- Documented follow-up schedule and complication management approach
- How long they track implants and how they handle long-term maintenance needs
If you are considering providers in multiple countries, also verify that:
- Your documentation (scan files, treatment plan summary, implant details) will be provided in a transferable format.
- There is a clear emergency contact pathway during the period when you are healing.
Step 6: Ask targeted questions (the “investment protection” checklist)
- What is the plan if the implant does not integrate as expected? Ask about timelines, additional interventions, and cost responsibilities.
- What is the warranty for the implant and for the crown/restoration? Clarify what is covered (and what is excluded, such as poor hygiene or non-attendance of follow-up).
- How will your bite be checked and adjusted? Ask whether occlusal adjustment is done at delivery and whether you have follow-up checks.
- What hygiene routine and recall intervals are recommended? Ensure they give you clear home-care instructions, including how to clean around the implant.
- Will orthodontic assessment be needed if you have spacing or bite discrepancies? If they propose not doing orthodontics, ask for the reasoning.
- What are the criteria for choosing immediate vs. delayed loading in your case?
- What are the expected healing milestones, and when should you contact them?
- Do they provide written aftercare instructions and a post-operative checklist?
By using this checklist, you protect yourself from “hidden” costs that emerge later and from unclear accountability if outcomes don’t match expectations.
8) Language-localized context: communicating clearly with patients
In practice, localized explanations can meaningfully affect decision quality. When a clinic provides patient-centered content in Spanish or Portuguese, it can reduce misunderstanding around timelines, risks, and maintenance responsibilities. This matters for implant outcomes because patients must follow post-surgical instructions and commit to hygiene and follow-up—especially during the first weeks and months when tissue maturation and implant stability are critical.
Clinics and insurance resources in Spanish and Portuguese markets often emphasize service categories such as orthodontics, whitening, implants, and emergency care—useful for patients who want a single organization to coordinate multiple dental needs. For English-speaking research, cost-focused portals and broader dental groups may help with process understanding and service availability.
Patient communication checklist (especially relevant for cross-border planning):
- Ask whether you can receive an explanation and consent forms in your preferred language.
- Confirm whether the clinic provides written aftercare instructions in your language (or whether you will need a translator).
- Request that your treatment plan summary (what was done, when, and with which materials) is provided in a way your home dentist can understand.
- If you attend follow-up locally after travel, provide the implant system details and prosthetic component information.
Language barriers can increase the chance of missed instructions (for example, medication timing, food restrictions, and hygiene steps). Clear communication can be an underrated “quality factor” alongside clinical factors.
9) Where Orthosmile Hounslow fits into the decision tree
For patients near Hounslow, a strong starting point is often a consultation that clarifies three things:
- Feasibility: whether you have adequate bone and periodontal conditions for implant placement.
- Integration with alignment: whether orthodontic planning would improve the final restoration fit and function (and whether it’s necessary, optional, or not needed).
- Cost transparency: what the quote includes (diagnostics, surgery, restoration, follow-up) and what could change after imaging review.
Even when patients later explore affordability options abroad, a local specialist assessment can help you understand clinical requirements so you can compare “like for like.” In other words, the consultation can function as a translation layer between your personal clinical needs and external pricing models.
To make that consultation maximally useful, consider asking:
- “If I want to reduce cost, what parts of the plan are adjustable and which parts are not?”
- “What is the minimum clinically acceptable plan for my case?”
- “Which diagnostic findings are driving the plan?”
- “What are my maintenance expectations and recall frequency?”
When you have answers to those questions, you can approach other providers with confidence that you are comparing plans based on the same clinical requirements. That is the best way to achieve lower costs without accidentally compromising clinical outcomes.
10) FAQs (expert-oriented and practical)
Q1: What should I ask during an initial Orthosmile Hounslow consultation for implants?
Ask for a treatment plan that covers diagnosis, imaging, implant positioning rationale, restoration design, and follow-up. Also request a clear itemized estimate: what is included in the quoted price, and what might require additional cost if clinical conditions differ after imaging review.
Useful follow-up questions include:
- “Can you show me the scan results and explain what they mean for implant positioning?”
- “What is the expected healing timeline in my case, and what milestones will we check?”
- “How will the bite be evaluated at delivery?”
- “If I experience discomfort or swelling outside the normal window, who should I contact?”
Q2: Is orthodontic treatment always required before dental implants?
No. Orthodontics is required only when alignment, spacing, bite mechanics, or prosthetic positioning would otherwise compromise the restoration. If adjacent teeth have shifted or you have aesthetic-zone concerns, orthodontic assessment may be recommended to optimize good outcomes.
For example, a clinician might suggest orthodontics if:
- The missing tooth area lacks adequate space for a crown with good proportions.
- The adjacent teeth tilt into the space, increasing the risk of a poorly angled implant restoration.
- The bite has a trajectory that would overload an implant crown.
But if adequate space exists and your bite can be harmonized through prosthetic design alone, orthodontics might not be necessary.
Q3: Can I get “low-cost” implants without reducing quality?
Lower cost can sometimes be achieved through efficient scheduling, appropriate treatment selection, or insurance/financing structures. The key is to compare full pathway costs—not only the implant fixture. Ask for documentation of planning, prosthetic materials, infection control approach, and warranty/follow-up.
A practical way to test whether “low cost” is legitimate is to request:
- An itemized breakdown of stages
- A written follow-up schedule
- Clear implant and crown material details
- A maintenance recommendation and recall plan
If those are missing, the quote may be cheap for reasons that could affect outcomes.
Q4: Are the country cost ranges accurate for my situation?
They are reference ranges only for planning. Your actual cost can change based on bone availability, the need for augmentation, implant number, whether you require a bridge, and the restoration design (including aesthetic demands). Always request a personalized quote after diagnostics.
Also consider exchange-rate variability and differences in what is included. A low-cost country quote may look appealing but may not include transportation, post-operative reviews, adjustments, or the costs your local dentist charges for follow-up.
Q5: What risks should I understand before choosing dental tourism?
The main risks relate to continuity of care, aftercare coordination once you return home, and differences in clinical protocols. If you pursue travel-based care, ensure you have a documented post-operative plan, emergency contact pathways, and clarity on warranty and follow-up responsibilities.
Additional risks to consider:
- Delays in complication management due to travel distance
- Communication problems between your travel clinic and your local home dentist
- Unclear responsibility if additional surgery or prosthetic repairs are required
- Different standards or practices for peri-implant maintenance that may affect long-term success
To reduce these risks, insist on detailed written documentation including implant brand/system, abutment type, crown material, and a timeline for follow-up appointments.
Q6: How do I evaluate whether a clinic’s quote is “complete”?
Request an itemized breakdown and confirm what happens at each stage. A complete quote should describe diagnostics, surgical procedures, restoration materials, timeline, follow-up schedule, and complication/warranty policy. If the quote is vague, request clarification in writing.
“Complete” should also include:
- What is included in the immediate post-operative period
- When suture removal (if used) is scheduled
- When prosthetic delivery is expected
- Whether occlusal adjustments are included and how many times you can return for adjustments
- Whether maintenance visits (or hygiene programs) are recommended and included or billed separately
Q7: Do insurance plans reduce dental implant costs?
Sometimes, depending on eligibility and plan rules. Insurance guidance resources typically help users understand coverage and how to apply for benefits. However, coverage varies widely; ask the insurer (or plan administrator) which implant-related services are included and whether pre-authorization is required.
When insurance is involved, ask your clinic to provide documentation such as diagnosis codes and treatment plan summaries that insurance needs for approval. If insurance requires that you use specific providers or specific implant types, check those rules early to avoid delays.
Q8: What is the role of maintenance after implants?
Maintenance is central to good success. Many clinically significant implant failures related to biologic factors are associated with peri-implant inflammation and inadequate hygiene. Establish a recall schedule and receive guidance on home care and professional monitoring.
Maintenance usually includes:
- Professional cleaning tailored to peri-implant surfaces
- Assessment of gum tissue health
- Monitoring of occlusion and bite forces
- Reinforcement of hygiene technique
- Early detection of inflammation so treatment can be started before advanced peri-implant disease occurs
11) Conditions, requirements, and decision criteria (what you should document)
Before you decide on any implant pathway—including options associated with Orthosmile Hounslow—consider compiling the following information. This helps you compare clinics fairly and reduces the chance that a “low-cost” quote misses key requirements.
- Your clinical findings: bone condition, periodontal status, imaging results, and risk factors (including smoking status and systemic conditions).
- Your restorative requirements: crown/bridge design goals, aesthetic expectations, and bite plan.
- Your timeline constraints: work schedule, travel commitments, and willingness to attend follow-up appointments.
- Your budget definition: what “low cost” means to you, and what trade-offs are unacceptable (for example, you might not accept skipping orthodontic assessment if it affects bite and restoration).
- Your support plan: who monitors healing, where you would go for urgent care, and how aftercare will be managed if you travel.
- Medication and health context: any long-term medication, allergies, and conditions that can affect healing (for example, diabetes control) and infection risk.
When you have these documented, it becomes easier to compare clinics fairly—whether you are evaluating a local provider or a cross-border pathway.
It can also help to keep a file (digital or paper) with:
- Radiology reports
- Written treatment plan summary
- Itemized estimates
- Warranty terms (implant and prosthetic)
- Aftercare instructions
12) Evidence-informed perspective: choosing reputable, verifiable care
In implant dentistry, reputable outcomes depend on more than marketing. Globally, professional bodies and consensus guidance emphasize thorough assessment, infection control, appropriate prosthetic planning, and structured maintenance. Patients can apply these principles regardless of geography by demanding clear diagnostics, a logical treatment rationale, and follow-up commitments.
What “reputable care” typically looks like in practice:
- Clear diagnosis and documentation: your clinician can explain what they see on imaging and why it matters for implant placement.
- A prosthetic-first mindset when appropriate: the plan considers the final crown/bridge position so the restoration is functional and hygienic.
- Risk management: your case is assessed for factors that influence healing and long-term success.
- Appropriate materials and technique: implant system selection, abutment design, and restoration materials align with clinical needs.
- Maintenance planning: you receive a recall schedule and hygiene education that match your risk level.
- Realistic timelines: your clinician explains healing windows and milestones, rather than promising instant results.
For insurance and patient education resources, it’s also wise to cross-check claims using official organization guidance where available. This reduces the chance of relying on incomplete or overly promotional summaries. A clinic that answers your questions clearly—even when you ask “hard” questions—often demonstrates better clinical governance.
How to spot red flags when comparing “low-cost” claims:
- They refuse to provide itemized pricing or written treatment plans
- They promise identical outcomes for different anatomies without explanation
- They minimize the importance of follow-up and maintenance
- They won’t discuss complication management or warranty terms
- They discourage getting imaging or second opinions when clinically appropriate
Red flags don’t always mean a clinic is unsafe, but they do indicate incomplete transparency. In healthcare, transparency is part of quality.
13) Disclaimer
1). The above information comes from online resources, and the data is as of October 2023.
2). Dental implant prices are for reference only and may vary by region, clinic and doctor.
References and links
https://dentalviews.com/low-cost-dental-implants/
https://www.atlanticdentalgrp.com/
https://www.dentavacation.com/
https://rockvilledentalarts.com/es/